Educational discussions linked to the clinical interests above.
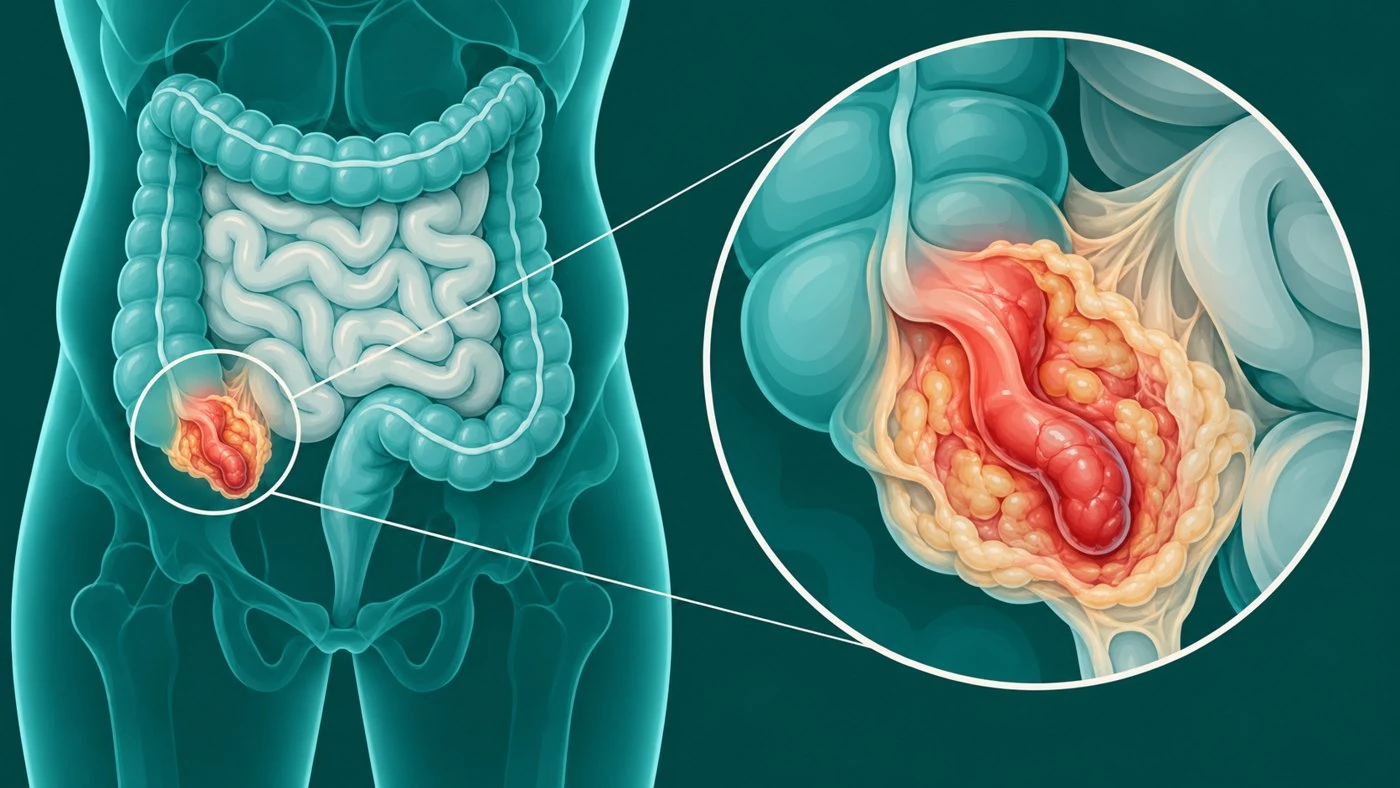 Surgical Decision-Making
Appendiceal abscess and phlegmon: an updated decision pathway
The 2025 WSES update changes the age-based abscess pathway and interval-appendectomy advice. Do not apply an older rule to every inflammatory mass.
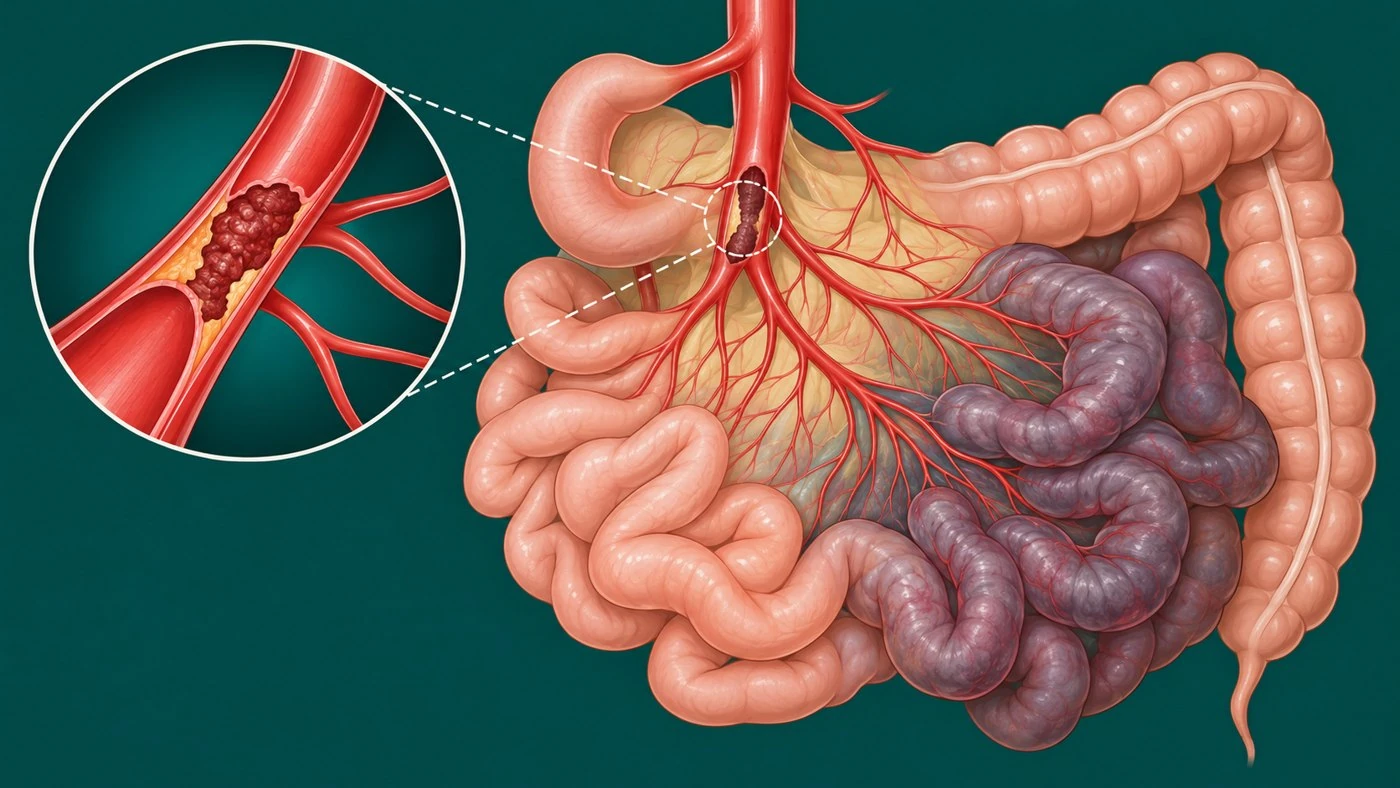 Clinical Case Discussion
Pain out of proportion: an acute mesenteric ischemia case discussion
A hypothetical case illustrates why an initially soft abdomen and a normal lactate must not delay urgent vascular imaging.
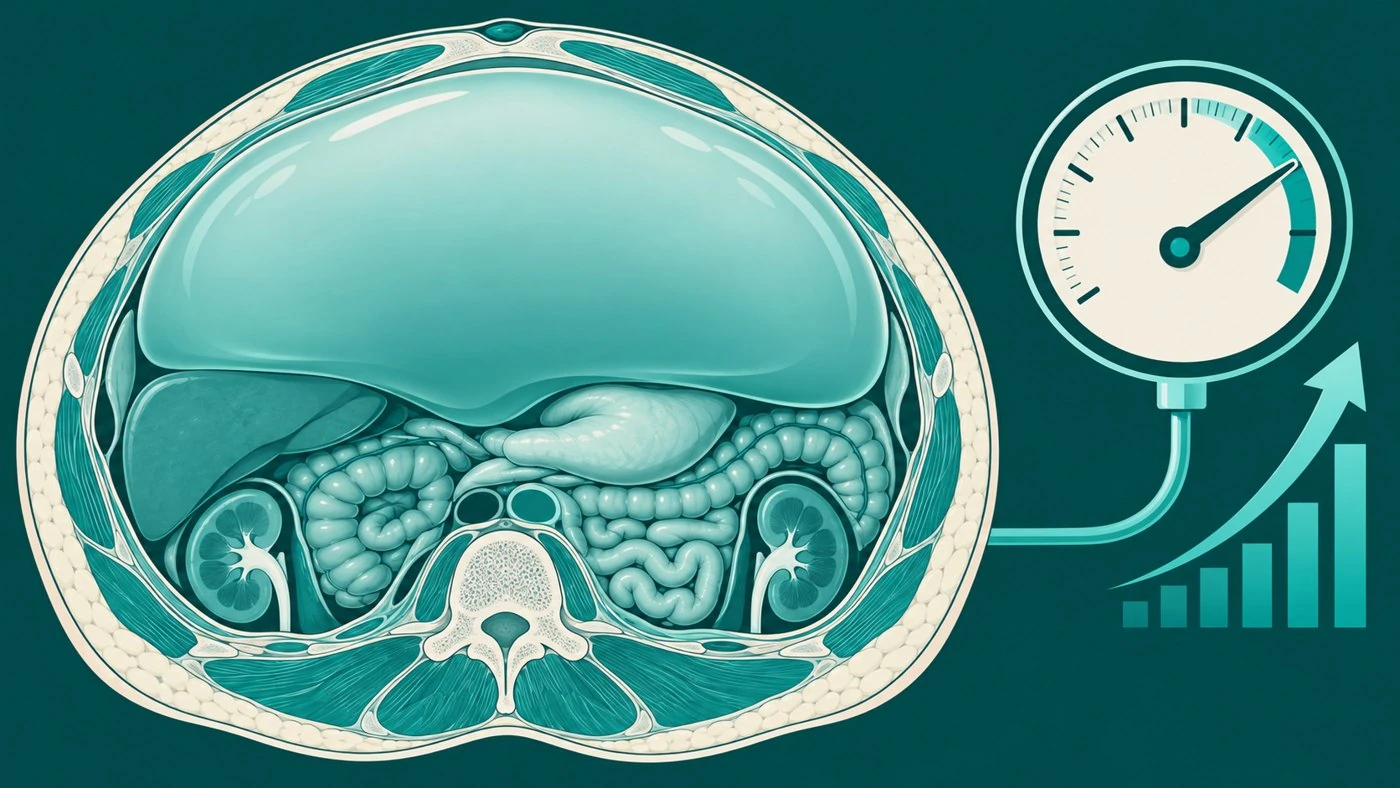 Surgical Decision-Making
Abdominal compartment syndrome: measure pressure, protect organs
A tense abdomen is a clue, not a measurement. Sustained pressure elevation with new organ dysfunction requires urgent action.
Surgical Decision-MakingAcute mesenteric ischemia: diagnosis, reperfusion, and bowel preservation
CTA, early specialist involvement, and cause-specific treatment are central. Not every mesenteric ischemia pathway requires the same intervention.
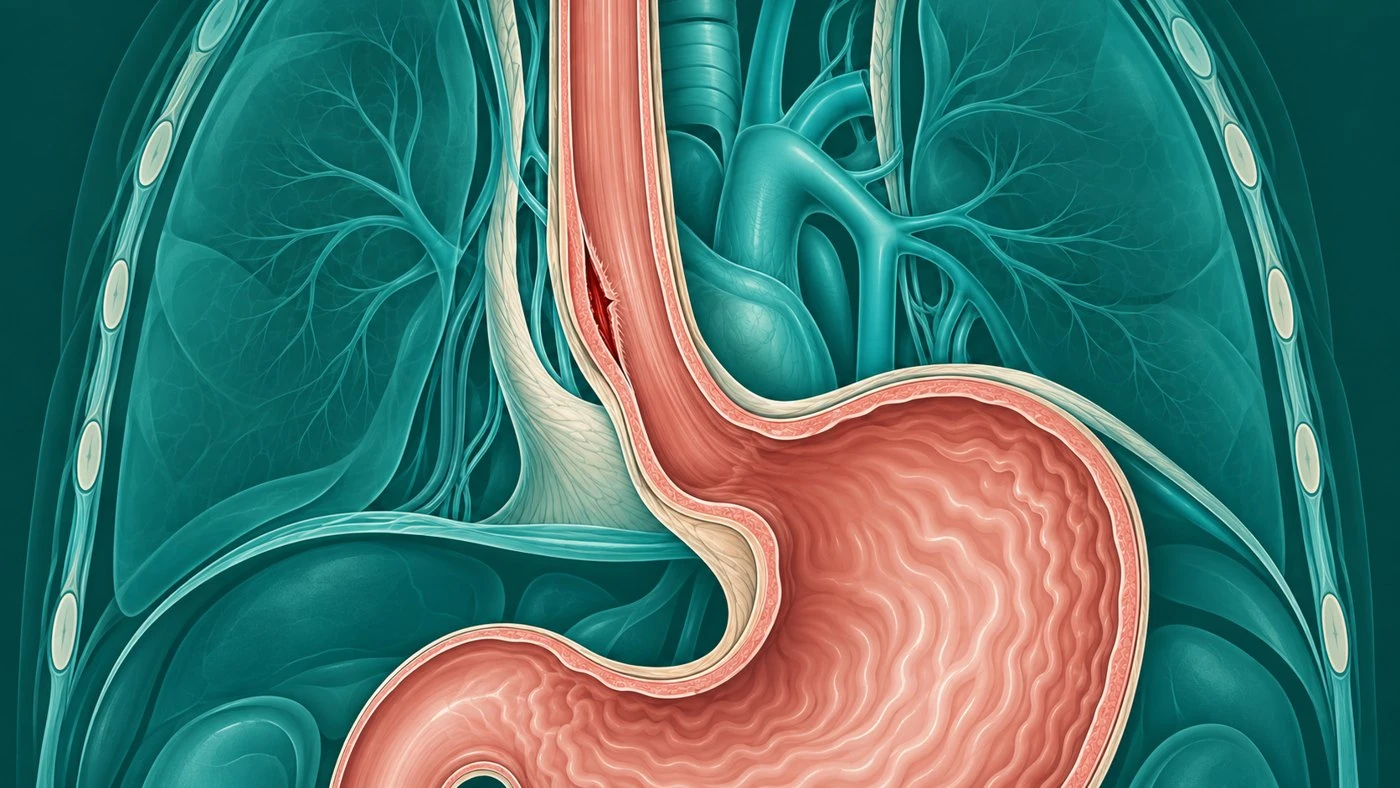 Surgical Decision-Making
Boerhaave syndrome: recognize perforation and control contamination
Chest pain after forceful vomiting warrants a broad emergency assessment. Treatment of esophageal perforation depends on physiology, containment, and expertise.
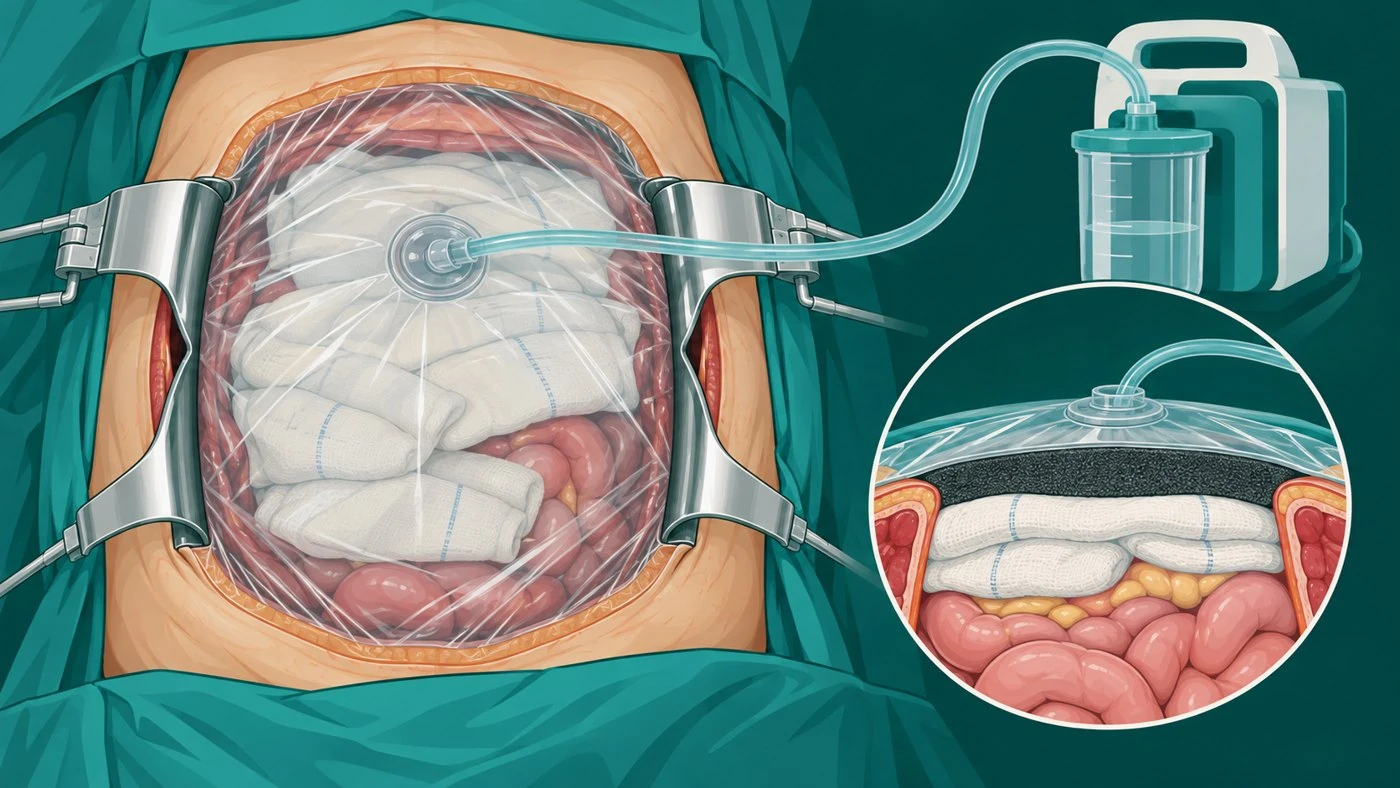 Surgical Decision-Making
Damage-control laparotomy: let physiology set the operative plan
An abbreviated operation can be lifesaving in selected critically injured patients, but an open abdomen also carries substantial risk.
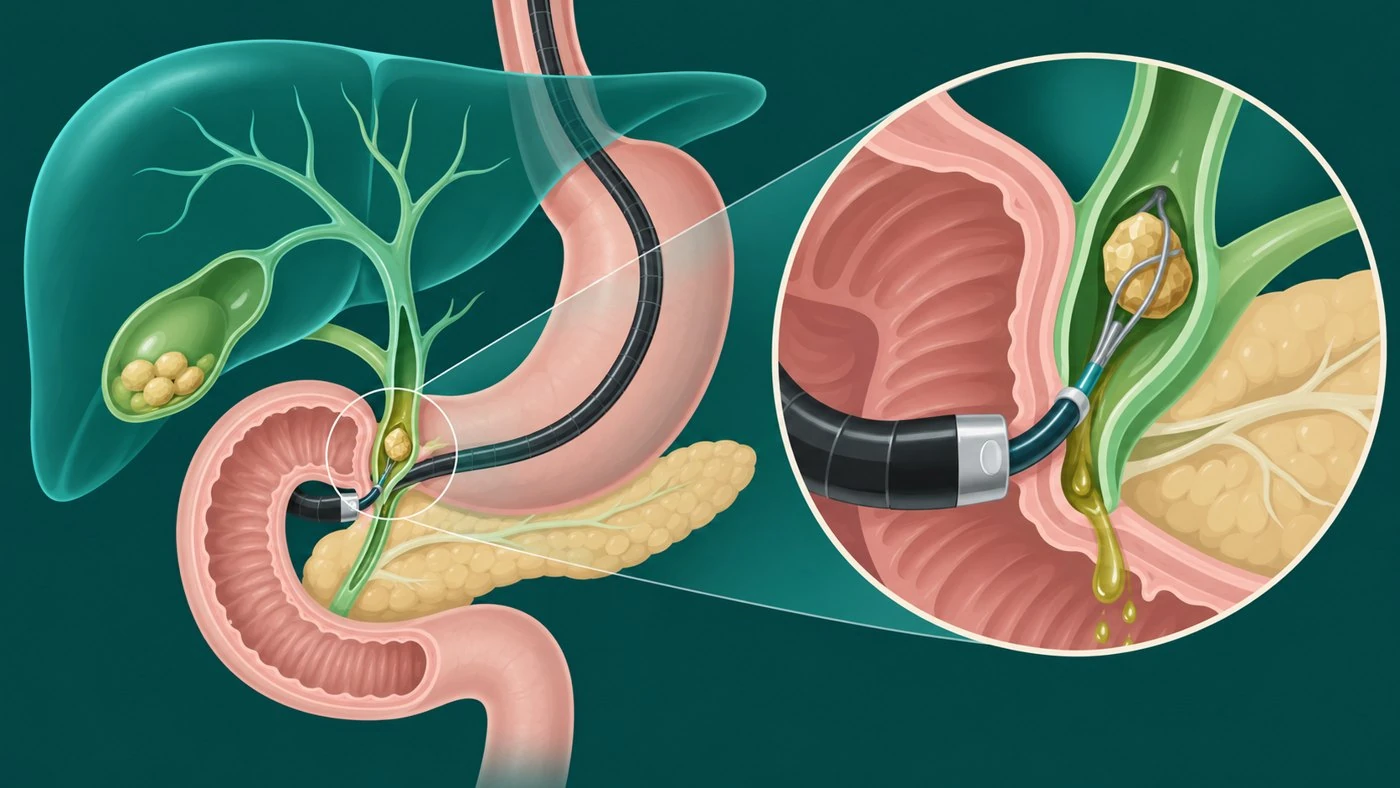 Surgical Decision-Making
Acute cholangitis: recognize sepsis and plan biliary drainage
Combine inflammation, cholestasis, and imaging rather than relying on a complete Charcot triad.
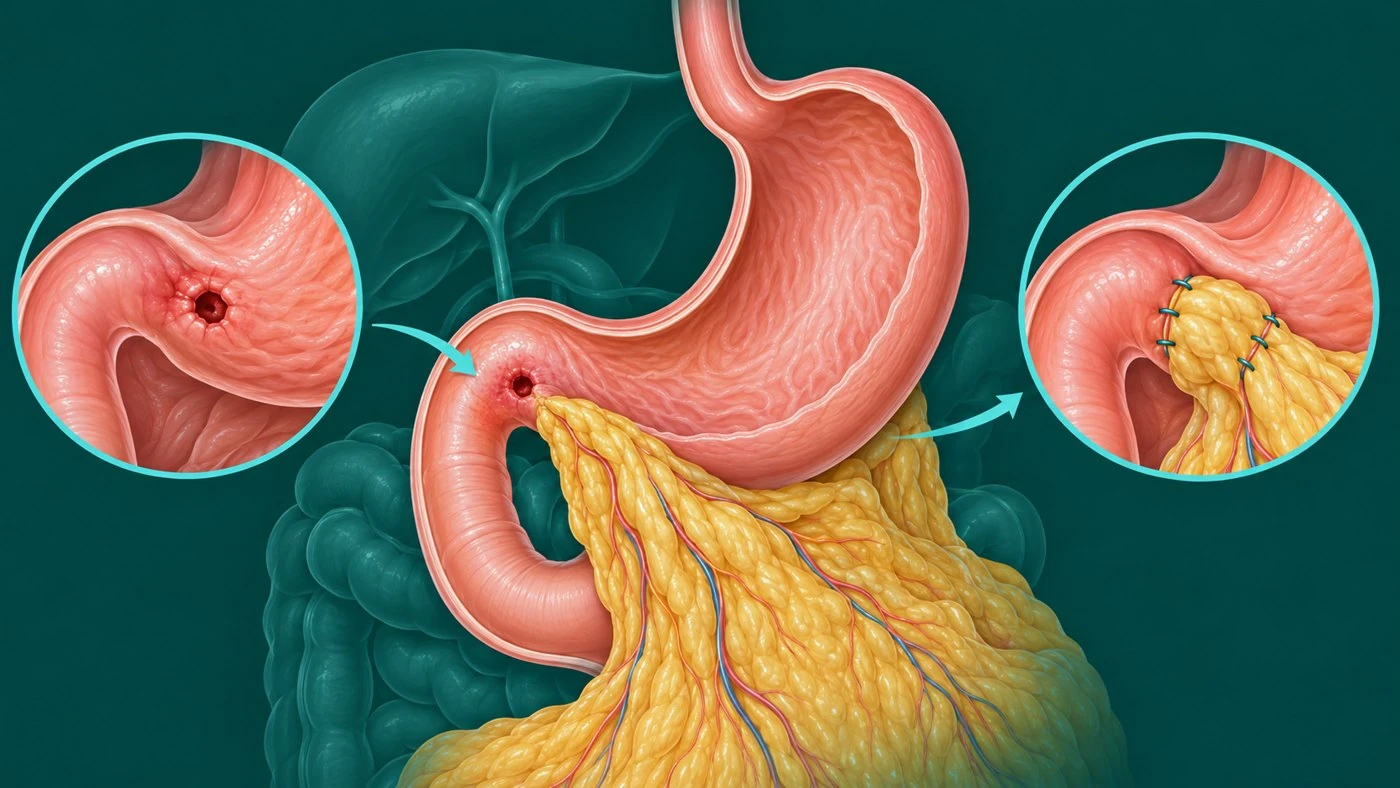 Surgical Decision-Making
Perforated peptic ulcer: timely diagnosis and individualized repair
Peritonitis and physiological deterioration drive urgency. A patch is an option, not a universal solution for every perforation.
 Surgical Decision-Making
Strangulated abdominal-wall hernia: recognize ischemia and inspect viability
A painful irreducible hernia with concern for ischemia needs urgent surgical assessment. Repair strategy depends on contamination and patient condition.
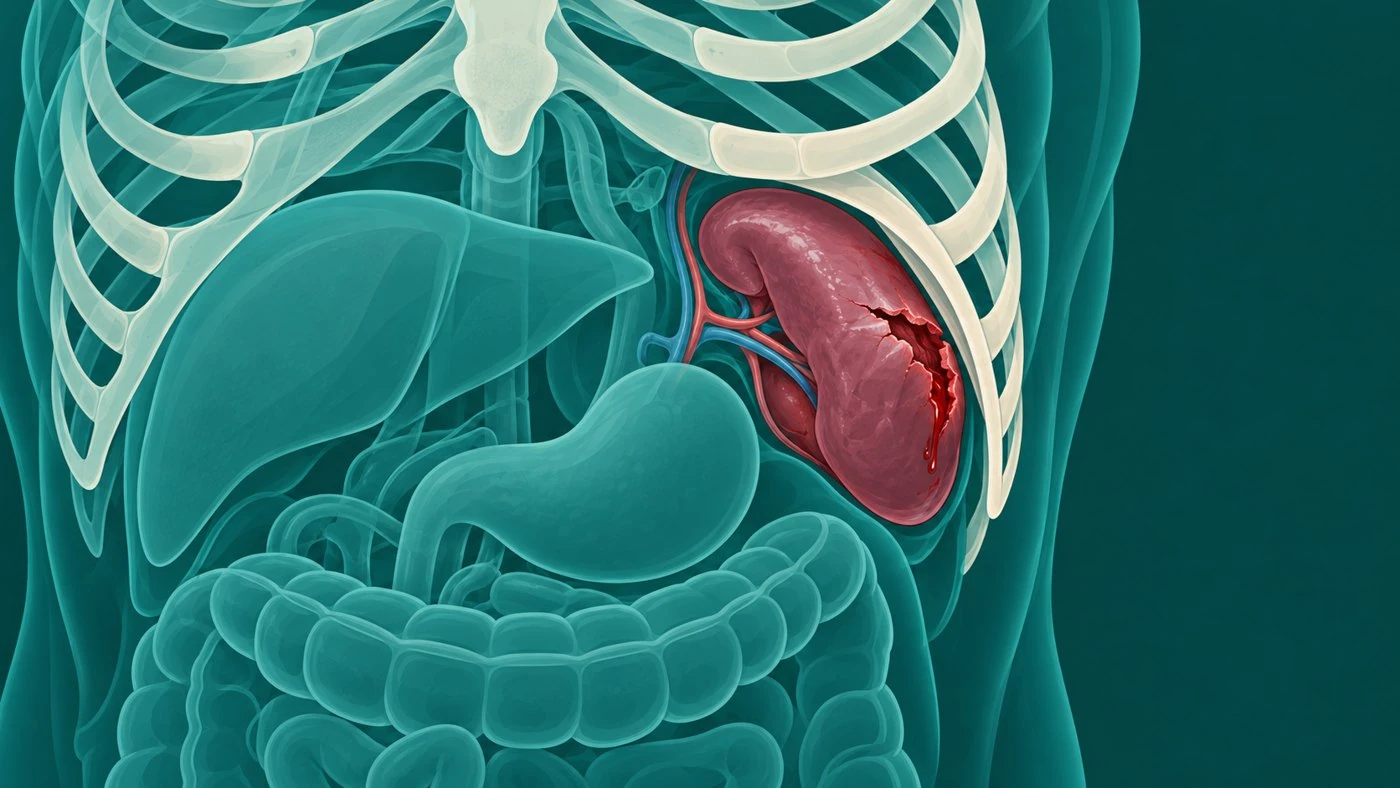 Surgical Decision-Making
Splenic trauma: physiology first, preservation when safe
Injury grade informs the plan, but hemodynamic response, associated injuries, and local rescue capability determine what is safe.
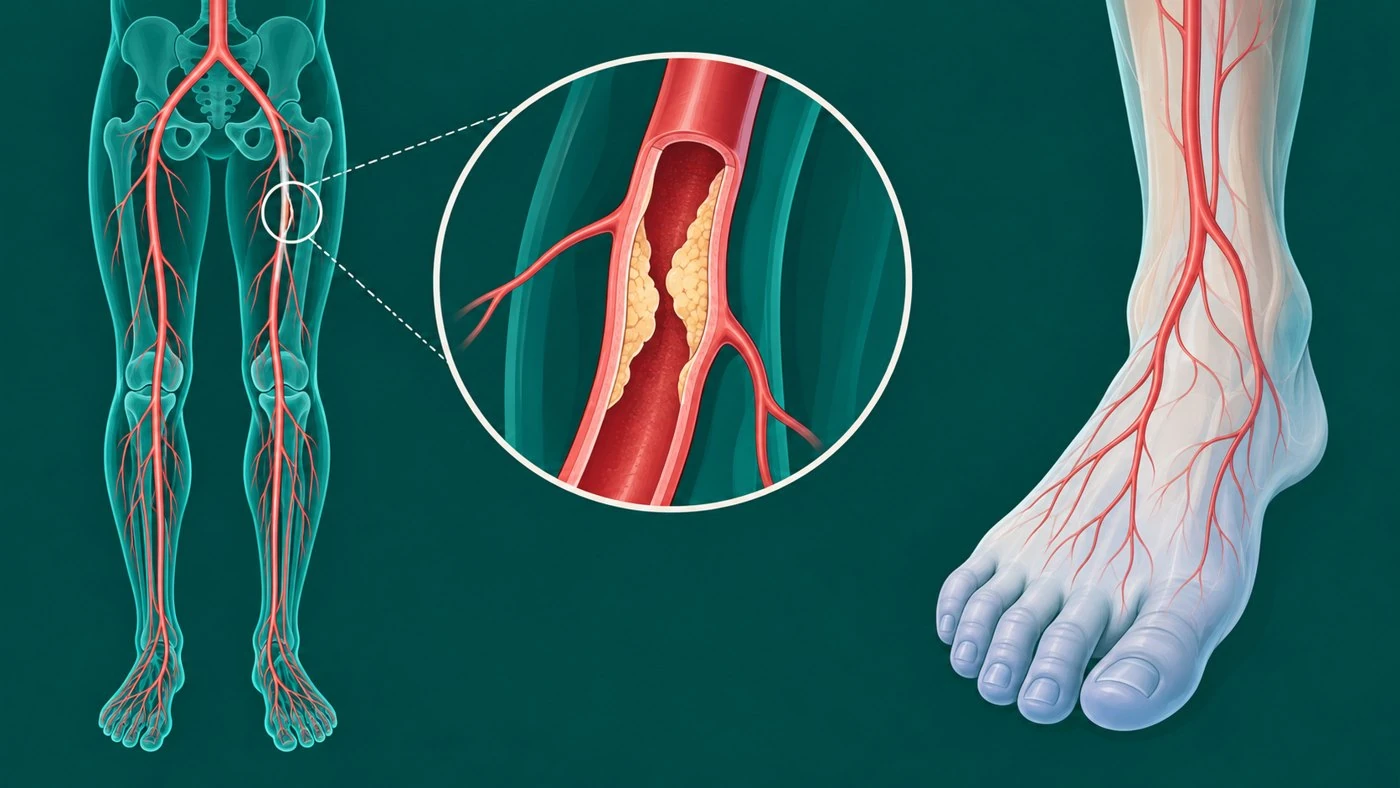 Surgical Decision-Making
Acute limb ischemia: let viability, not the clock alone, guide urgency
Sensory and motor findings help distinguish a viable limb from one requiring immediate reperfusion. Six hours is not a universal biological deadline.
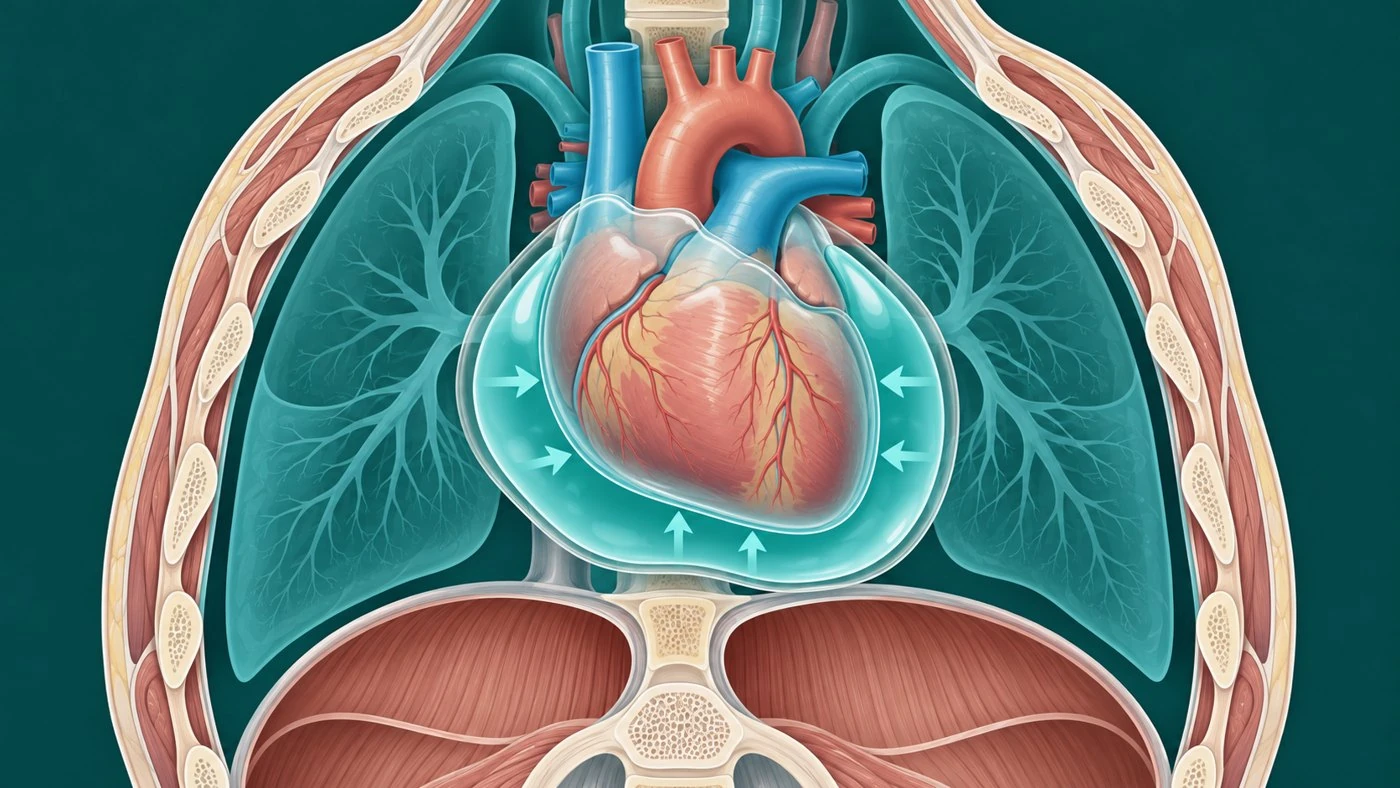 Clinical Case Discussion
Traumatic cardiac tamponade: recognize obstructive shock and mobilize surgery
A hypothetical penetrating-trauma scenario illustrates why absent neck-vein distension and an incomplete Beck triad cannot reassure.
